Wednesday, 31 January 2018

Two steps back for tobacco harm reduction

Last week the FDA was advised to keep it a secret that iQOS is safer than smoking, and the European Court of Justice was advised to keep snus illegal. I've written an article for Spectator Health about the anti-science, freedom-hating prohibitionists responsible.

There seems to be a principal-agent problem when new nicotine products are assessed by people who are steeped in ‘public health’ dogma, especially when those products contain tobacco. Bates argues that ‘panel members have strong ‘virtue signalling’ incentives to oppose tobacco industry innovation, even if highly beneficial to people at greatest risk. They can enter the room, turn up the pedantry dial to maximum, sit back and relax, lob in the odd insincere question and vote down the claims, all the time faking an appearance of trying to do the right thing.’

And so we have two products which are manifestly less harmful than cigarettes, both of which have a track record of getting people to stop smoking. One is illegal in the EU. The other is illegal in the USA. Neither of them can be labelled as less harmful and neither can be marketed as a reduced-risk product. At best, the government prevents manufacturers from putting truthful statements on these products. At worst, it prevents them from selling them at all.

Do have a read.


Tuesday, 30 January 2018

The anti-drink lobby's war on reality: Geordie Shore edition

Some more puritanism dressed up as academia for you, this time from Alcohol and Alcoholism...

Alcohol Content in the ‘Hyper-Reality’ MTV Show ‘Geordie Shore’

Three tax-spongers from the UK Centre for Tobacco and Alcohol Research (UKCTAS) watched an entire series of the Newcastle-based reality show Geordie Shore and were - as the stars of this show might say - 'proper radge' to find numerous depictions of alcohol use.

All categories of alcohol were present in all episodes. ‘Any alcohol’ content occurred in 78%, ‘actual alcohol use’ in 30%, ‘inferred alcohol use’ in 72%, and all ‘other’ alcohol references occurred in 59% of all coding intervals (ACIs), respectively. Brand appearances occurred in 23% of ACIs. The most frequently observed alcohol brand was Smirnoff which appeared in 43% of all brand appearances. Episodes categorized as suitable for viewing by adolescents below the legal drinking age of 18 years comprised of 61% of all brand appearances. 

Shocking stuff, I'm sure you'll agree.

Alcohol content, including branding, is highly prevalent in the MTV reality TV show ‘Geordie Shore’ Series 11. Current alcohol regulation is failing to protect young viewers from exposure to such content.

Note the focus on 'young viewers'. I am not familiar with Geordie Shore but from what I've heard it is not exactly a children's programme. It is broadcast on MTV at 10pm and Series 11 is rated 18 on DVD. When I looked at the official website I found a selection of video clips with titles such as 'WTF! Gaz and Abbie neck on in naked hot tub party', 'Chloe's boob flash and char confession' and 'Scott finger blasts Chloe'.

It is, however, the use of alcohol that troubles our trio of researchers. They watched all 425 minutes of Series 11 and kept a count of every example of 'actual use, implied use without actual use, paraphernalia without actual or implied use, and brand appearance (real or fictitious)'.

Imagine having that much time on your hands. Imagine being paid to do it (the funders for this crucial scientific research were British Heart Foundation, Cancer Research UK, the Economic and Social Research Council, the Medical Research Council and the Department of Health).

The fruits of their labour can be seen below. As you can see, there is a fair bit of alcohol use and 'inferred alcohol use' in between the fighting, swearing and shagging in Geordie Shore.


I'm sure you're as keen as I am to know what inferred alcohol use, so here's a handy chart.


The authors then go through every permutation of their findings in autistic detail before announcing that...

The findings of this study demonstrate that the occurrence of alcohol content (verbal and imagery) and alcohol brand appearances is highly prevalent in ‘Geordie Shore: The Complete Eleventh Series’ (GS11).

I expect a fan of the show could have told us that without being given money by the British Heart Foundation, but now it's official.

Similarly, our previous research found alcohol, including branding, to be the prevalent in contemporary music videos...

The life of a 'public health' scientist, eh?

Only one question remains: 'SO WHAT?!' And the authors spend the rest of their article telling us why we should give a hoot.

The study also found that alcohol content and alcohol brand appearances occurred in all episodes of the series deemed suitable for viewing by young people below the age of 18 years. The legal drinking age in the UK is 18 years.

The age at which you can buy a drink is 18 years, yes. Watching somebody else have a drink, on the other hand, is not age-restricted - and only a lunatic would suggest it should be.

Just because you're not allowed to do something doesn't mean that you're not allowed to watch somebody else do it on television. This basic distinction seems to have gone over the heads of our friends at the UK Centre of Tobacco and Alcohol Research.

This is an important finding...

It really isn't.

...because the drinks industry should be adhering to its own self-regulatory codes of practice which aim to prevent exposure of their products to an underage audience.

The drinks industry doesn't produce Geordie Shore, though, does it? As far as we know, no alcohol company has any involvement with it.

However, the regulation of alcohol advertising in the UK has already been criticized for systematically failing by producers and agencies exploiting the ambiguities in the codes (Hastings et al., 2010).

Regardless of whether that's true - and if you're citing Gerard Hastings it probably isn't - Geordie Shore is not covered by alcohol advertising regulation because - guess what? - it's not advertising. It is a reality TV show about twenty-somethings in Newcastle and - guess what again? - the reality is that they drink.

The authors then list various companies' code of conduct for advertising as if it's got anything to do with the real or inferred use of alcohol in reality TV shows:

Anheuser-Busch InBev, the leading global brewer, produces and sells over 200 beer brands globally (AB InBev, 2015). It owns two brands that appeared in this study; Corona and Budweiser. They have a voluntary marketing code that states ‘we are dedicated to promoting smart consumption and reducing the harmful use of alcohol’ (AB InBev, 2016) The code does not apply to television programmes that use their products without express permission to do so, which may have occurred in GS11. Drinks distributer Diageo is the global leader in alcohol beverages (Diageo, 2017). It owns five alcohol brands recorded in the data: Smirnoff, Captain Morgan, Baileys, Tanqueray and Cîroc. Diageo state that marketing will only be placed ‘where 71.6% or more of the audience are expected to be older than the legal purchasing age’ (Diageo, 2016). Clearly this is not guaranteed in GS11. Heineken UK and Bacardi Limited, the owners of Grey Goose, make similar claims in their corporate responsibility policies (Grey Goose, 2015; Heineken, 2015).

All totally irrelevant to the matter at hand.

It is unclear whether the drinks manufacturers have paid for brand advertising in GS11, in which case several codes of practice have been clearly violated...

'It is unclear whether' translates as 'There is no evidence that', so I think we can dismiss that option and move on to the more likely conclusion:

...or if this is a form of de facto advertising where brands are unofficially advertised without the alcohol producer’s knowledge...

Bingo! Now we're getting somewhere. The participants drink alcohol in real life and so that's what the programme shows.

...in which case it is surprising that the companies have not objected and demanded withdrawal of their products.

I guess they could request that the labels be covered up, but it would make them look like control freaks for no benefit to anybody. The viewer would still be exposed to 'inferred drinking' and 'on-screen drinking to excess, with related drunk and disorderly behaviour and sexual encounters', which is what the researchers are supposedly concerned about.

Finally, and as usual in 'public health' studies these days, the conclusion is devoted to a shopping list of new laws and regulations that the authors want to introduce.

...enforcing new policy measures to help protect adolescents from alcohol imagery in the media is essential. Given that 60% of GS11 episodes were awarded by the BBFC and age rating of 15 years, it appears that the existing age classification policy is not protecting young people from alcohol imagery and its potentially harmful effects. 

As mentioned above, you have to be 18 to buy the DVD of Geordie Shore. The authors are talking about the ratings of individual episodes, some of which are rated 15. This is enough for them to play the think-of-the-children card.

In any case, there is no age limit on exposure to 'alcohol imagery'. Alcohol advertisements can be shown at any time of day on British television, except during children's programmes. Geordie Shore is on at 10pm at night, as I mentioned above but the authors mention do not at all (they merely say it is on during 'primetime'.)

The BBFC should award reality television programmes, which include excessive alcohol content and which promote excessive drinking and/or brand placement, an age rating of 18+ years.

The BBFC will not give something an 18 rating just because it depicts heavy drinking. They are not nuts. They did not cave in to Mary Whitehouse and they are not going to cave in to a small band of anti-drink zealots. They have patiently explained why they are not going to start giving 18 ratings to films that depict smoking and much the same applies to drinking. We do not ban films that depict murder just because murder is banned. Similarly, we do not give adult ratings to programmes that depict drinking, smoking or gambling just because you have to be an adult to do these things yourself.

A fairly simple concept to grasp, I would have thought. Now be gone with you.


Sunday, 28 January 2018

Nick Cohen's dystopia

Nick Cohen has gone on a health kick and thinks that his midlife crisis should form the basis of public policy. Previous victims of this delusion include Sarah Vine, David Aaronovitch and, a few days ago, Jenni Russell. After Cohen gave up drinking last year, he wrote a factually inaccurate article calling for more temperance laws. He is now running a half marathon and has decided that the British population must forced to do more exercise.

The results are fairly terrifying. His latest Observer column begins like this:

If you imagine a healthy future for Britain, or any other country that has put the hunger of millennia behind it, you see a kind of dictatorship. Not a tyranny, but a society that ruthlessly restricts free choice. It is a future that views the mass of people as base creatures jerked around by desires they cannot control. Expert authority must engineer their lives from above for their own good and the common good.

This is literally Orwellian, with the opening sentence evoking the famous line from 1984: 'If you want a vision of the future, imagine a boot stamping on a human face - forever.' And whilst you might expect Cohen to draw back from this explicit authoritarianism and say something along the lines of 'but that would not be reasonable' or 'only kidding!', his article continues in exactly the same vein. Towards the end, he reasserts:

When we imagine a healthier future we are also imagining a more authoritarian state. Individual choice will be constrained and wisdom of the crowd rejected.

If this is the deal on offer, many of us would say that you can stick your 'healthy future' and give us liberty. It is doubtful whether the choice is as binary as Cohen suggests: despite all the wailing about obesity, people's health continues to improve whereas none of Cohen's coercive policies have been shown to work - but he seems to believe what he says and he takes it as read that people should be prepared to sacrifice liberty for longevity. As I wrote in Killjoys, this is a core belief of the 'public health' lobby despite the fact that nobody makes such an extreme trade-off when left to their own devices.

His overarching justification for forcing lifestyle change upon the population is the usual excuse about poor diets and lack of exercise bankrupting the NHS (may peace be upon it). Anyone who knows the economics of longevity understands that this is piffle (have a read of Death and Taxes for a summary). But, having fallen for this popular myth, he then launches into his programme for change:

Here’s my partial sketch of how Britain would have to change to limit the costs to the NHS that stunted lives and avoidable pain will bring. Pedestrians and cyclists would have priority on the roads. If the roads are too narrow to take cars, cycle lanes and a pavement wide enough to allow pedestrians to walk or run in comfort, then cars will have to go. 

Roads are obviously not too narrow to take cars, so I can only assume that Cohen will extend cycle lanes to make them so. I assume this because...

It will not necessarily be illegal to drive in towns and cities, just pointless. Motorists would inch along because cycle and bus lanes would take up road space and pelican crossings would be reset so pedestrians never had to wait more than a minute to cross a road. 

This is an idea that can only be seriously entertained by someone who works from home in central London. How practical would it be to bring Britain's roads to a standstill in an effort to force people to walk?

Let's look at some statistics. 89 per cent of all journeys in Britain are taken by road and two-thirds of business/commuting trips are taken by car. Only 6 per cent of car journeys are under a mile and the majority of journeys under a mile are already taken on foot. Even if we leave aside the foul British weather, the weight of luggage and the need of vans and lorries to make deliveries, the distances involved are simply too long.

Incidentally, although I don't have the stats for this, life experience tells me that pedestrians at pelican crossings do not have to wait more than a minute to cross the road.

Even when they reached their destinations, drivers would search forever for a space because car parks would have been demolished and replaced with public parks.

Because everyone lives within a mile of their workplace and should just get on their bloody bike, eh Nick? Never mind all the people who live in the suburbs, small towns and countryside - who are, by the way, in the majority.

Cohen's logic suggests that closing down railways, bus routes and the tube would also be necessary to get Britain exercising and yet he does not mention any of these. Perhaps the idea of getting around London without the help of an engine is not as appealing as the vision of suburban drones marching to the office?

School runs will become history as heads refuse to admit any able-bodied child who arrives at school in a car.

What about those who arrive in a bus? Is motorised transport only acceptable if it is owned by the state?

No fast-food outlet would be allowed within a one-mile radius of a school. 

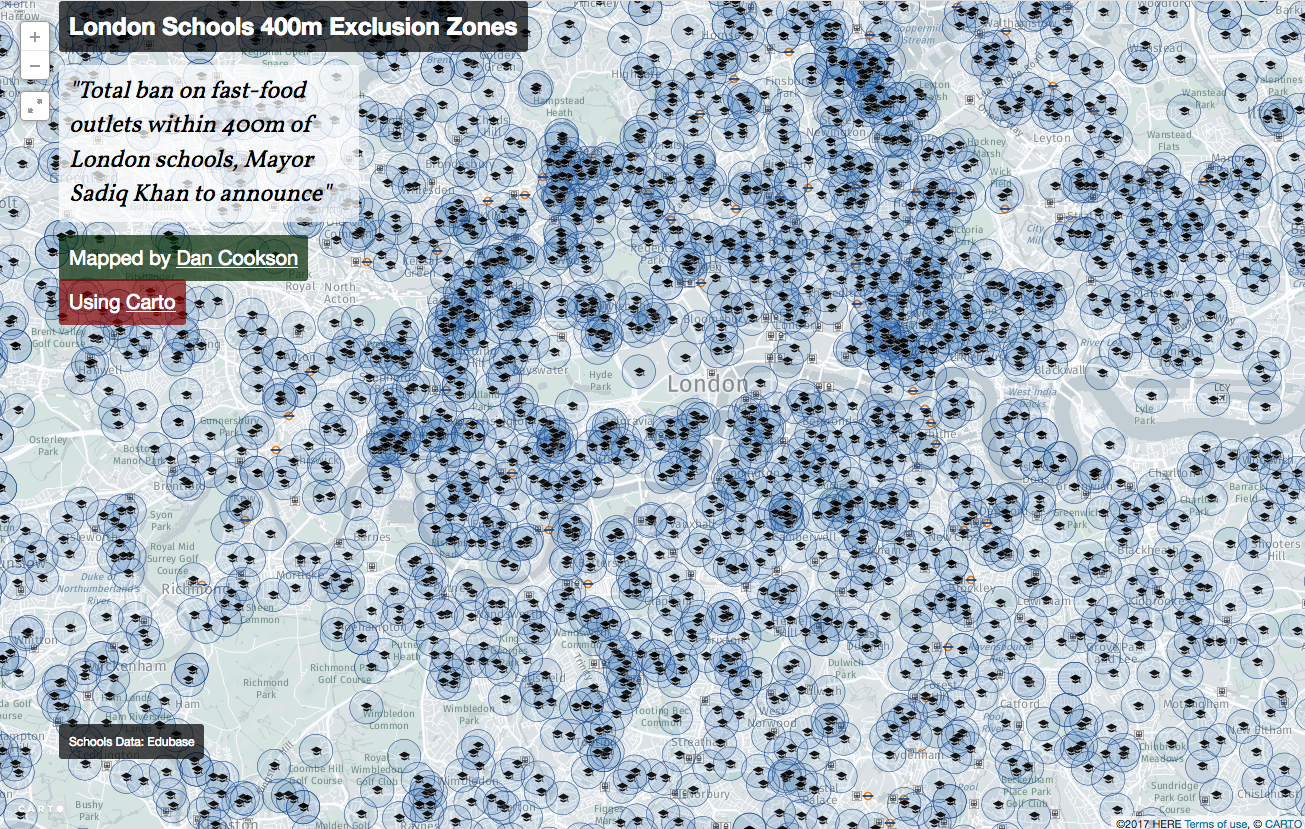
Effectively, this would mean no fast food outlets in Britain's towns and cities. Thanks to Dan Cookson, we know what an exclusion zone of 400 metres around schools - as proposed by Sadiq Khan - would look like.


Cohen is proposing an exclusion zone that is four times wider than this and that applies to all fast food outlets, not just the new ones. This would amount to a total ban on shops selling pizzas, hamburgers, fish & chips, kebabs etc. Cohen would probably be happy with that, but it sounds a tad heavy-handed.  

Agricultural subsidies for fat and sugar would be abolished. 

There are no subsidies for 'fat'. Fat is a component of most food products including meat, cheese and milk. In so far as there is a subsidy for sugar, it is part of the EU's farming regime of tariffs and subsidies which, on balance, makes sugar more expensive that it would otherwise be.

Rapeseed oil and sugar beet cultivation would stop as new subsidies for public transport began. 

I have no idea what he is talking about here. Is he suggesting that the government ban the farming of these crops? Or does he think that people will spontaneously stop consuming them when public transport is (further) subsidised? If so, why? There is no logical connection between the two, but the call to subsidise public transport confirms that it is private car ownership, not physical inactivity, that is really bugging Cohen.

Meanwhile, the manufacturers of processed food high in sugar, salt and fat would face advertising bans and punitive taxes. (If food manufacturers want to dump prematurely sick patients on the NHS, we will say, they can damn well pay for the privilege.)

Food manufacturers don't pay excise taxes, consumers do.

It may seem a less practical measure but I would hope to see a vigorous challenge to the paradox of our culture’s celebration of thinness and athleticism in an overweight world. The idealisation of film stars and athletes raises impossible expectations. Because 99% of people do not have the genes – or the time and money for training – to even think of imitating them, we simply don’t try. A small blow could be struck if UK Sport were forced to stop sponsoring elite Olympic athletes and spend its millions on sports facilities for all instead.

Again, I have no idea what he's talking about it. Whilst I am extremely sympathetic to the idea of not paying people to participate in the jingoistic tedium of the Olympics, I fail to see how withdrawing the funding will make us any thinner. It is wibble.

Sugar and fat addiction, like all addictions, provide a temporary respite for the poor, the depressed and the disappointed. 

Sugar and fat addiction do not exist. Giving up something you enjoy and then missing it does not make you an addict.

Perhaps we should offer them better lives rather than snatch away the few comforts they enjoy. 

That would be nice wouldn't it? But you have no way of doing it and you're only going to make their lives worse by dishing out the kind bans and taxes as that evil billionaire Mike Bloomberg threatened us with this week.  

This sounds a stirring counter-argument. 

It's better than taxing the hell out of us, censoring the media, and making us walk for miles in freezing temperatures, yes.

But as any reader who has been an addict will know, addiction prevents you finding a better life.

People are not addicted to driving and there is no evidence that they have a latent demand for cycling, walking or tasteless food.

God knows, there are good reasons to mistrust experts re-engineering societies from above.

Given that the main 'expert' Cohen cites is a fanatic called Tim Lang who thinks that repealing the Corn Laws was a mistake and believes that making food more expensive is an admirable end in itself, this mistrust is justified.

But as with tobacco, freedom of choice in the food and car markets has left us with no choice but to trust them.

The vilification of 'car markets' is a new one to me, but it is no surprise to see tobacco being used, once again, as a precedent for controlling the lives of private citizens.

Cohen admits that many readers will regard his proposals as 'dystopian', and so they are. Nevertheless, I am glad that he has put them down on paper. His article is a fine reminder of what we are up against.

Friday, 26 January 2018

Junk alcohol research of the week

Sometimes the junk science that comes out of the ‘public health’ lobby is so bad you just have to laugh. Take this study, for example, published yesterday in the apparently reputable Journal of Hepatology. As reported by the Irish Times, it found that ‘alcohol consumption even at very low levels early in life may significantly increase the risk of alcoholic liver disease in men’. It was even suggested that drinking guidelines should be lowered to accommodate this emerging evidence.

Alcoholic liver disease is a relatively rare condition that overwhelmingly affects very heavy drinkers. It would be surprising, to say the least, if ‘very low levels’ of drinking caused it.

And yet the media’s coverage of this study accurately reflected the claims made by its authors. They claim to have shown that ‘consumption of alcohol early in life is associated with an increased risk of developing severe liver disease in men’. They say that ‘men consuming as little as one to five grams [less than one unit] of alcohol per day had an increased risk of severe liver disease compared to abstainers, indicating that the increased risk of severe liver disease might be present even at very low doses of alcohol.’ Moreover, they declare – in the abstract of the study – that: ‘Current guidelines for safe alcohol intake in men might have to be revised.’

How did they arrive at these remarkable conclusions? First, they dug up some old documents from the Swedish army dating back to 1969-70 when conscription was still in force. These documents contain survey data from conscripts aged between 18 and 20, including estimates of how much they drank.

This gave the researchers the baseline figures for alcohol consumption. The men were then ‘followed for a mean period of 37.8 years’ to see what happened to them. This is a rather grand way of saying that the researchers looked at Sweden’s National Patient Register to see how many had developed alcoholic liver disease by 2009.

Of the 43,296 individuals who had provided drinking estimates in 1969/70, 383 had developed severe liver disease (0.9 per cent). When the researchers looked at their alcohol consumption, they found that those who drank the most were the most at risk and those who did not drink at all were the least at risk. Fair enough but, more surprisingly, they also found that those who only drank one or two units a day were at increased risk.

The authors describe these findings as ‘borderline statistical [sic] significant’. In fact, they are nowhere near being statistically significant, but we’ll leave that to one side. The more interesting question is this. In the 39 years between the men being recruited to the army and their medical records being examined, how often do you think the researchers asked them how much they drank?

Every six months? Once a year? Once every five years?

How about never? Because that’s how often they kept abreast of what these men were drinking. Not once. They have no idea how much their subjects’ drinking behaviour changed in the intervening years. All they know is that the people who were teetotal in 1970 were less likely to develop liver disease than the people who were drinkers in 1970. Hold the front page!

In no way does this study show, or even imply, that drinking at low levels causes liver cirrhosis. The authors’ suggestion that their study shows that ‘recommendations for safe alcohol consumption regarding the risk for development of severe liver disease in men might be set too high’ is an absurd non-sequitur.

Quite obviously, the men in this study did not continue drinking at the same level as their 19 year old selves for the rest of their lives. Some of the teetotallers became heavy drinkers (we know this because eleven of them developed alcoholic liver disease), some of the heavy drinkers became teetotallers, and some of the light drinkers became heavy drinkers. It is not drinking at ‘very low levels early in life’ that causes the damage. It is drinking at very high levels later in life. Without knowing anything about what these men were drinking after 1970, the study tells us precisely zero about the relationship between alcohol and liver disease, nor does it inform the discussion about what a ‘safe level’ of drinking is.

Why are journals publishing this pointless rubbish? Judging by the lead author’s comments to the press, the aim is not to tell us anything useful, but to put pressure on the Swedish government to follow the UK in lowering the drinking guidelines.
“If these results lead to lowering the cut-off levels for a ‘safe’ consumption of alcohol in men, and if men adhere to recommendations, we may see a reduced incidence of alcoholic liver disease in the future,” Dr Hagström said.
It would be strangely fitting if the Swedes lower their drinking guidelines based on junk science which claims that alcoholic liver disease is a threat to light drinkers. As the e-mails released under the Freedom of Information Act show, it was only by making this scientifically illiterate assumption that the UK’s Chief Medical Officer was able to lower the guidelines in 2016.

We can expect more studies of this kind in the next few years. The anti-drink lobby will not be happy until the official drinking guidelines are zero and they will go to any lengths to achieve it.

[Cross-posted at Spectator Health]

Tuesday, 23 January 2018

Snus goes to court again

I was interviewed for the Europeans Podcast recently about the issue of snus. You can listen to it here (iTunes) or here (Android).

The interview was timely because we've just had news out of Norway where Sweden's experience of a mass cross-over from cigarettes to smokeless tobacco has been replicated.

More Norwegians use snus – a form of snuff particular to Nordic countries – instead of cigarettes for their nicotine fix, official figures showed for the first time on Thursday.

The preference for snus in Norway, is certain to revive debate over the health effects of the product, a moist powder tobacco that is popped under the lip.

Though its sale is illegal across the EU, it is manufactured and used in Sweden, which has an exemption, and Norway, which is not an EU member.

According to Norway’s statistics office SSB, 12% of Norwegians used snus daily in 2017, compared with 11% who smoked cigarettes every day.

Uber-tweeter Stephen Fry has also posted one of his occasional tweets on the subject:


On Thursday, the EU's ban on snus will be tested at the European Court of Justice. As I described in The Art of Suppression, the ECJ ruled that the ban was legal some years ago after the IARC rushed out a briefing which conflated snus with hazardous smokeless tobacco products from places like India. Since then, more epidemiology has shown snus's potential to help smokers quit and has found the product to be vastly less hazardous than cigarettes.

The case has been brought by Swedish Match and the New Nicotine Alliance. The latter has issued an update on its website:

The case was originally brought by Swedish Match. The New Nicotine Alliance asked to be joined to this case because it concerns the health of smokers in the European Union. It is not about markets and commerce, but about the right to be able to choose a safer alternative to smoking. For the NNA this case is about whether some 320,000 premature deaths from smoking can be saved in future years, as detailed by Dr Lars Ramström in his statement to the court.

The denial of access to lower risk snus leads to unnecessary deaths. The NNA believes that smokers have a right to safer nicotine products as alternatives to smoking and the right to make choices that help them avoid adverse health outcomes.

The core of the NNA’s case is that the ban on snus is both disproportionate and contrary to the right to health. There is no need for the ban, and the ban, if upheld, will continue to contribute to excess mortality from smoking in Europe.

This is the first time that a ‘right to health’ argument has been used to challenge a bad tobacco law: we argue that the Court needs to examine the compatibility of the Tobacco Products Directive with both the EU Charter of Fundamental Rights and the harm reduction obligation under the Framework Convention on Tobacco Control.

I have written before about how Brexit offers an opportunity to get rid of this ridiculous ban, but the ECJ case offers an opportunity for smokers across the EU to switch to snus.

Fingers crossed.

Monday, 22 January 2018

A junk history of tobacco harm reduction

An article in Tobacco Control by a pair of professional anti-smokers from San Francisco asks why the US and UK have such different approaches to e-cigarettes and other reduced-risk nicotine products.

Major British health organisations support tobacco harm reduction for smokers struggling to quit. The USA, in contrast, classifies e-cigarettes as tobacco products and leaders are less supportive of tobacco harm reduction.

Historians have attributed this transatlantic difference to the tobacco industry’s long history of deception over ‘safer’ products resulting in scepticism towards tobacco harm reduction.

Have they? That's news to me. Elias and Ling cite three articles as proof, but only one of them was written by a historian and that was published in 2004, long before e-cigarettes hit the market. None of them makes the argument that Elias and Ling say they do.

But never mind because the rest of the article makes the argument - such as it is - anyway. They do this by going over the story of the Independent Scientific Committee on Smoking and Health (ISCSH) which conducted safer cigarette research with the tobacco industry in Britain in the 1970s. The story they tell has been mostly drawn from the excellent work of the historian Virginia Berridge. You can read a very short summary of the initiatives of the 1970s in Vaping Solutions, but the gist of it is that nothing really came of them because smokers tend to draw more deeply on low tar cigarettes and regulation prevented more imaginative safer cigarettes from succeeding in the market.

Elias and Ling go through the British experiments for several pages and then, finally, get to the point:

In the eyes of the broader British public health community, the ISCSH work was largely for naught. Yet in recent years, the Committee’s guiding logic and premises of risk reduction have enjoyed a reanimation among British public health organisations.

Hear that dog whistle? The message is 'once bitten, twice shy'. History is repeating. Beware!

British public health should mind past experience, in which industry-backed ‘safer cigarettes’ undermined public health.

Elias and Ling argue that efforts in the UK to make cigarettes safer were an industry-led distraction which caused the British government to shelve effective anti-smoking policies. By contrast, the USA got on with the job of clamping down on cigarettes and had no truck with tobacco harm reduction.

As if that weren't bad enough, it's all happening again. When will those limeys learn?

If the past is any guide, the promotion of tobacco harm reduction may serve the interests of tobacco companies more effectively than the public.

The problem with this narrative is that it's ahistorical nonsense from start to finish. It turns a blind eye to the inconvenient fact that America had its own industry-government working group that spent millions of dollars trying to make cigarettes safer. The US National Cancer Institute set up the Tobacco Working Group in 1968 (five years before ISCSH was formed) for this very purpose, but the only acknowledgement of this in the Tobacco Control article is one sentence in the discussion section:

Government and industry collaborations to develop a ‘safer cigarette’ were not unique to the UK. From 1968 to 1979, the US National Cancer Institute spent US$50million to sponsor the Tobacco Working Group (TWG).

Government-approved efforts to launch safer cigarettes in Britain and the US were effectively dead in the water by 1978 and 1979 respectively. The two countries did not have different experiences and, therefore, their different attitudes to tobacco harm reduction today cannot be explained by them.

Moreover, the USA did not choose tough anti-smoking measures over tobacco harm reduction, and the UK did not choose harm reduction over anti-smoking policies. From the 1980s to the present day, the UK has had higher tobacco taxes, more restrictive advertising laws and larger health warnings. It also managed to ban snus, the only viable reduced harm product that existed until e-cigarettes came on the scene.

Elias and Ling's little morality tale is a travesty of history and explains nothing. Britain's approach to tobacco harm reduction, and vaping in particular, doesn't require much explanation. From around 2012, lots of smokers spontaneously switched to vaping and the government ultimately decided that this was a good thing. 

Britain is not unique in this. Across the developed world, governments have recognised the benefits of vaping and have regulated e-cigarettes accordingly, ie. more lightly than cigarettes. The sale of e-cigarettes is now legal in every EU country, for example, albeit with some silly restraints from the EU. The USA is the outlier insofar as it has moved from a tolerant position to a more extremist one. It is this American exceptionalism that requires an explanation.

My explanation is that US policy has been influenced by people, such as those at Elias and Ling's Center for Tobacco Control Research and Education, who are more interested in fighting tobacco companies than in fighting smoking. There is also a stronger puritanical element in the US anti-smoking movement than there is in the UK, and America has a stronger history of prohibition. Furthermore, the pharmaceutical industry has more clout in the US than it does in the UK and funds anti-smoking groups to a much greater extent.

In both countries, the 'public health' lobby is divided between those who are genuinely interested in health and those who are, in effect, moral or political crusaders. In Britain, the former just about managed to gain the upper hand, despite opposition from the likes of Martin McKee and Simon Capewell. In the USA, the latter are in charge. They are all awful, illiberal people to varying degrees, but in America the very worst have risen to the top.

Friday, 19 January 2018

Blame the government, not Brexit, for the biscuit rip off

McVitie's are reducing their packets of Digestive biscuits from 500g to 400g. This means consumers will be getting seven fewer biscuits in their pack. Parts of the media have been blaming Brexit for this and the company itself has pointed the finger at the weaker pound and rising cost of raw materials.

McVitie's is shrinking the size of a packet of Digestives because of price increases caused by the Brexit drop in the pound, it claims.

The company said the value of sterling has made ingredients more expensive and it did not want to damage the quality of the biscuits.

If these were the real reasons, the obvious thing to do would be to raise the price. If companies made their products smaller every time inflation rose, everything would be tiny.

But they are not the real reasons. When the ONS looked at the 'shrinkflation' of chocolate and confectionery last year, it found no evidence that the value of sterling or the price of raw materials were responsible:

Manufacturers’ costs may also be rising because of the recent fall in the value of the pound – leading some commentators to attribute shrinkflation to the UK’s decision to leave the European Union. But our analysis doesn’t show a noticeable change following the referendum that would point towards a Brexit effect. Furthermore, others (including Which?) had been observing these shrinking pack sizes long before the EU referendum, and several manufacturers have denied that this is a major factor.

The real blame lies with Public Health England and its sugar reduction scheme. PHE have set the food industry the target of reducing sugar in its products by 20 per cent by 2020. McVitie's said last year that it was 'confident' it could achieve this.

But how? Artificial sweeteners do not work well in biscuits. When PHE realised that genuine product reformulation was impractical, they told the companies that reducing portion size would count as sugar reduction. Indeed, they actively encourage them to reduce portion size.


Shrinking a pack of biscuits from 500g to 400g is a reduction of twenty per cent and so McVitie's can claim to have met its target. Last year it reduced the number of Jaffa Cakes in a packet from 12 to 10, which is nearly a twenty per cent reduction. There will be more to come.

The price of the new, smaller pack of Digestives is also going to be reduced, but not by as much. It will fall from £1.25 to £1.15, a drop of 8 per cent. The result is that Public Health England can say that their target has been met, McVitie's can make a bit more money and the consumer loses out. Meanwhile, people who don't want to leave the EU can brandish this as further evidence that Brexit is making us all poorer.

But it is fake news. It has nothing to do with Brexit. It is all about the government's ridiculous childhood obesity strategy. They call it 'health by stealth'. Doing it by stealth is bad enough, but denying that it is happening while lying about the reasons behind this rip-off is intolerable.